

- Scheduling
- Eligibility
- Provider workflow
- Patient communication
- AI Receptionist
- Task automation
Behavioral Health Practice Operating System
Manage the Complete
Patient-to-Payment Cycle
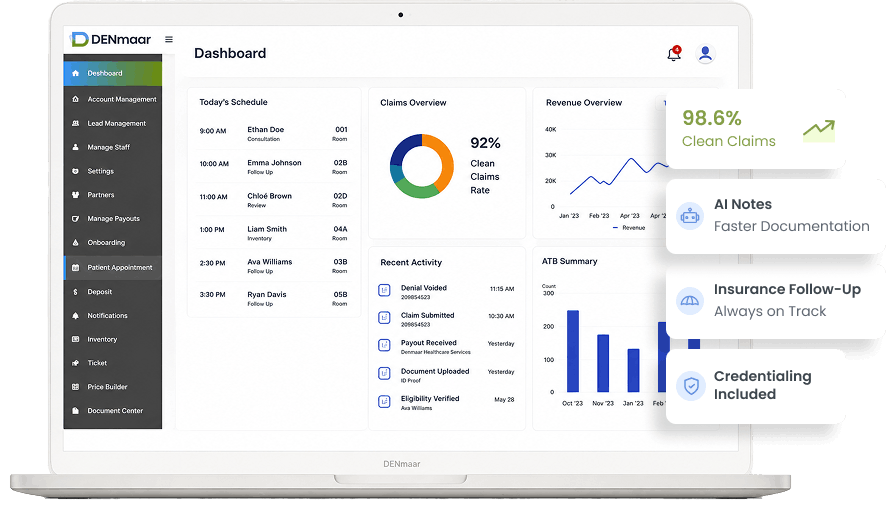
From the first patient call through scheduling, documentation, claims, and payment, DENmaar connects the work of your practice and automates routine steps.

Run your entire practice from one intelligent platform backed by behavioral health expertise.

AI-powered workflows
Behavioral health expertise
ONE INTEGRATED PLATFORM
Four Solutions. One Platform.
Everything growing behavioral healthcare organizations need to run a modern practice.
AI Clinical Documentation
Create therapy, psychiatry, group, and multidisciplinary documentation in minutes with AI designed specifically for behavioral healthcare.
Revenue Cycle Management
Professional insurance billing, payment posting, denial management, patient responsibility, eligibility verification, credentialing, and financial reporting.
More than software.
A complete revenue cycle solution.
AI Practice Automation
Administrative work should happen automatically whenever possible.
Insurance Knowledge Team
Healthcare reimbursement is constantly changing. DENmaar includes access to an expanding insurance knowledge platform built specifically for behavioral healthcare.
Get guidance on:
- Coding
- Prior authorization
- Documentation
- Claim resolution
- Medical necessity
- Credentialing
- Insurance requirements
- Best practices
Built from thousands of real-world behavioral health billing scenarios.

BUILT TO SCALE WITH YOU
Designed for Growing Practices
Whether you’re adding your second provider or expanding into multiple locations, DENmaar grows with your organization.
Start simple.
Get up and running quickly with the essentials.
Add capabilities
Unlock advanced features as your needs grow.
Never outgrow
A platform that scales with your vision.

THE DENMAAR DIFFERENCE
Why DENmaar?
Most vendors sell software. Others sell billing services. DENmaar combines technology, AI, revenue
cycle management, and behavioral health expertise into one integrated platform.
Most vendors sell software.
Technology without the operational expertise to connect the pieces.
Others sell billing services.
Services without the intelligent platform to automate your practice.
DENmaar combines it.
Technology, AI, revenue cycle management, and behavioral health expertise into one integrated platform.
Enterprise Capability.
Small Practice Simplicity.
Schedule Your Personalized Demo
See how DENmaar can help your practice grow with confidence.
Let’s Determine Whether There Is Operational Alignment
We begin with a discussion focused on:
- Organizational structure
- Insurance workflows
- Operational goals
- Implementation fit
Request Information
Capterra, Software Advice And Get App 2023 / 25
Best Of Badges Awarded To DENmaar
2023 / 25 “Best of” badge winners = DENmaar Neuro has earned a well-deserved Best Value Badge.
See our reviews for our software being recognized as an impactful solution for your business.





Our Latest Blogs
Chatbots vs Agentic AI in EHR and RCM Systems: Understanding the Difference
Artificial intelligence is becoming part of the conversation around electronic health records (EHRs) and revenue cycle management (RCM). But answering a question and completing a workflow are different capabilities.
For a behavioral health practice, that difference matters. A useful answer can save time. A system that helps move work toward completion can change how the practice operates.
Agentic AI in EHR and RCM Systems
A chatbot provides a conversational interface. Depending on its connections and permissions, it may answer questions, explain information, summarize records, or draft content.
A provider might ask, “What documentation is still incomplete?” A billing specialist might ask, “What does this denial reason mean?”
An assistant connected to the appropriate data could identify unsigned notes or explain a denial. Staff would then take the next steps.
Instead of only explaining an authorization issue, an agent could check the authorization record, compare it with upcoming appointments, create a follow-up task, and route it to the appropriate employee.
Agentic AI can use connected tools to pursue a defined goal through multiple steps. It can select an available action, examine the result, and determine what should happen next within its permissions.
Instead of only explaining an authorization issue, an agent could check the authorization record, compare it with upcoming appointments, create a follow-up task, and route it to the appropriate employee.
These are illustrative possibilities, not claims that every EHR or RCM platform offers them today. For a broader look at agentic AI in behavioral health, the focus is on how carefully defined AI assistance could support everyday practice workflows.
Chatbots and Agentic AI: The Capability Difference
The distinction is also more nuanced than “chatbots talk, agents act.” A chatbot can be the interface through which a user directs an agent. What matters is the capability behind the conversation: which records it can access, which tools it can use, and how its work is controlled.
For provider documentation, conversational assistance could list incomplete notes and summarize what needs attention. An agentic workflow could prioritize outstanding work, open the relevant items, and route reminders or review tasks.
For authorization tracking, conversational assistance could explain recorded visit limits and dates. An agentic workflow could compare authorization data with scheduled services and assign exceptions for review.
For claim denials, conversational assistance could summarize a denial and suggest possible next steps. An agentic workflow could retrieve related claim details, prepare a follow-up task or draft correction, and route it for approval.
For patient billing, conversational assistance could explain a balance using available account information. An agentic workflow could check unresolved insurance activity and prepare an approved outreach workflow for staff review.
The benefit is fewer manual handoffs between identifying an issue and addressing it.
Agentic AI in EHR Workflows Needs More Than Automation
However, a scheduled reminder or a fixed rule is ordinary automation. It does not become agentic simply because a vendor adds an AI label. Agentic behavior involves selecting next steps based on the goal, available information, and results.
In an EHR or billing system, action needs accountability.
A practical design should limit access by role, record what the AI did, and clearly show what was completed, what failed, and what still requires attention. Missing or conflicting information should trigger review rather than a confident guess.
Clinical decisions, note signatures, coding changes, claim submissions, and financial adjustments need controls appropriate to their consequences. An agent may prepare work while a qualified person retains approval authority.
Eligibility results also should not be presented as a guarantee of payment. Moving faster does not remove the need to verify the underlying information.
Agentic AI in EHR: A Practical Starting Point for DENmaar
For DENmaar, the Provider Work Area is a practical place to connect conversational assistance with the work providers need to complete.
A useful first step is helping a provider see what needs attention and reach it more easily. Further development can focus on specific workflows where AI can prepare, route, or complete approved steps.
Success should be measured through everyday results: fewer clicks, fewer unresolved tasks, less duplicate work, and more timely completion.
The question practices should ask is simple: Does the AI only describe the work, or can it help move the work forward with clear permissions and visible results?
That is the difference that matters.
The healthcare workflow examples above are proposed applications, not documented DENmaar product capabilities.
Background Sources
OpenAI Agent definitions-> https://developers.openai.com/api/docs/guides/agents/define-agents
OpenAI Running agents-> https://developers.openai.com/api/docs/guides/agents/running-agents
OpenAI Guardrails and human review-> Guardrails and human review | OpenAI API
Frequently Asked Questions
What is Agentic AI in EHR systems?
Agentic AI in EHR systems can use approved tools and information to help complete defined workflows while keeping human oversight.
How is a chatbot different from Agentic AI?
A chatbot mainly provides conversational assistance, while Agentic AI can pursue defined goals through multiple approved workflow steps.
Can Agentic AI automate EHR workflows?
Agentic AI can potentially prepare, route, or complete approved workflow steps, depending on system access, permissions, and controls.
Can Agentic AI replace healthcare staff?
Agentic AI is designed to reduce repetitive work. Clinical decisions and other consequential actions should retain appropriate human oversight.
Why does Agentic AI matter for RCM?
It can help connect issue identification with follow-up, reducing manual handoffs and helping billing teams focus on unresolved revenue-cycle work.

Agentic AI in Behavioral Health: Helping Run Better Practices
Behavioral health practices have plenty of software. What they need is more help getting the work done.
An appointment needs confirmation. An intake packet remains incomplete. A provider has unsigned notes. A claim is waiting for information. Each issue may appear somewhere in the system, but someone still has to find it, understand it, and move it forward.
That is where agentic AI could make a meaningful difference in behavioral health.
How far away is it? Our view is that focused assistance is possible today. Dependable support across an entire organization will develop workflow by workflow.
From Answering Questions to Agentic AI Helping Complete Work
A chatbot gives people a conversational way to interact with software. An AI agent adds the ability to use approved tools, take steps toward a goal, check the results, and ask for help when needed.[1]
For a behavioral health practice, that could eventually mean asking:
“Help us prepare for tomorrow’s appointments.”
A connected agent could check for missing intake forms, identify records that need staff review, and prepare a prioritized task list. With the appropriate permissions and review process, it could also help initiate follow-up.
These are potential use cases, rather than capabilities we are announcing with our chatbot launch.
The value would come from reducing the effort between recognizing a problem and resolving it.
The Best Starting Points Are Everyday Tasks
We believe the most useful early applications will be specific, repeatable tasks with clear outcomes:
- Appointment preparation: Identify missing information before a visit.
- Provider workflow: Organize outstanding documentation and follow-up tasks.
- Billing coordination: Surface incomplete information holding up a claim and route it to the right person.
- Practice management: Summarize outstanding work so leaders can see where attention is needed.
Consider an unsigned note. Today, a staff member may discover it, locate the provider, send a reminder, and check again later. A future agent could help coordinate that sequence, while the provider remains responsible for reviewing and signing the documentation.
Small improvements like these could add up across a busy practice.
The Challenge Is Connecting Agentic AI to Real Operations
A convincing conversation is only the beginning.
To act reliably, AI needs access to the right information, permission to perform specific tasks, and a way to verify that its actions succeeded. Staff need to see what happened and intervene when something requires judgment.
A missing form and a clinical decision require different levels of oversight. Our approach is to start with bounded administrative work and expand only as each use case proves useful and dependable.
Success should be measured through fewer manual touches, less outstanding work, and more time available for patient care.
DENmaar’s Next Step Begins This Month
This month, DENmaar will introduce a chatbot feature.
That launch is an initial step toward making interaction with our system more conversational. It will also give us an opportunity to learn which questions and requests matter most to the practices using it.
From there, our direction is to identify specific workflows where AI can provide useful assistance, then build and evaluate those capabilities deliberately.
We see a practical path forward: begin with conversation, connect it to useful information, and progressively enable carefully defined actions.
For practices looking at a broader operating model for behavioral health, the opportunity is to connect AI assistance with the workflows that already move patients and work through the organization.
Behavioral health practices deserve technology that helps work move forward. Agentic AI brings that possibility closer, and everyday practice workflows are where we believe it can earn its place.
Background Source
[1] Anthropic, Trustworthy agents in practice. Supports the distinction between conversational assistance and agents that plan, use tools, check results, and seek human input. The proposed behavioral health use cases and DENmaar development direction above are editorial projections, not claims of currently released agent capabilities.
Frequently Asked Questions
What is agentic AI in behavioral health?
Agentic AI can help complete defined tasks, use approved tools, check results, and escalate work when human judgment is needed.
How can agentic AI help behavioral health practices?
It could help organize appointments, documentation, billing tasks, and other repeatable workflows while keeping staff involved in important decisions.
Is agentic AI available in healthcare today?
Focused AI assistance is already possible, while broader agentic workflows are developing gradually with defined permissions and human oversight.
What is the difference between AI and an AI agent?
AI can generate or analyze information. An AI agent can also use approved tools, take actions, check results, and seek human input.
How should practices adopt agentic AI?
Start with specific, repeatable administrative workflows where outcomes are clear, then expand as each use case proves useful and dependable.

A Connected Operating Model for Behavioral Health Practices: The Patient to Payment Cycle
A behavioral health practice does not operate as a collection of separate departments. A patient enters through a call, a message, a referral, or an online request. That interaction starts a chain of work that continues through scheduling, insurance, care, documentation, billing, and payment.
Most technology divides that chain into separate tools and queues. The front office answers the call. A scheduler books the appointment. Clinical staff document the service. Billers determine whether the claim can be submitted. When information is missing, people send messages, update spreadsheets, and wait for replies.
The problem is not that each person failed to do a task. The problem is that no system owns the complete journey. DENmaar calls that journey the Patient-to-Payment Cycle. It provides one operating model for moving every patient from first contact through completed care and collected revenue.
One Operating Model for Behavioral Health
The Patient-to-Payment Cycle connects patient access, clinical operations, and revenue cycle management. Each step prepares the next one. Information captured during the first conversation should support scheduling. Scheduling should initiate intake and insurance verification. The completed visit should trigger documentation, claim validation, submission, payment posting, and follow-up.
When these functions share the same workflow, staff no longer need to reconstruct what happened. The system can show the current status, identify what is missing, assign the next action, and measure the revenue affected by a delay.
AI Receptionist Begins the Cycle
The AI Receptionist is the front door. Its purpose is broader than answering the telephone. It should recognize the patient’s need, identify whether the practice can serve that patient, match the request to the right provider, schedule the appointment, collect insurance information, and begin intake.
A standalone voice assistant can take a message. An integrated receptionist can act on the practice’s real operating information: provider availability, specialties, state licenses, accepted plans, appointment rules, and service requirements. That difference determines whether automation reduces work or merely creates another queue for staff to review.
The Visit Must Be Ready Before It Begins
An appointment on the calendar is not necessarily ready for care. Eligibility may be inactive. Authorization may be missing. The selected provider may not be enrolled with the patient’s plan. Intake forms or insurance cards may still be incomplete.
A connected system should identify those issues before the appointment. Routine gaps can trigger automated reminders or requests. Only unusual situations should reach staff. This allows the practice to protect the patient’s experience while reducing the manual work that normally surrounds each visit.
Documentation Becomes Part of Revenue Integrity
Clinical documentation is often treated as a separate obligation. In practice, it is one of the conditions required for payment. The provider needs a clear work area showing today’s patients, notes due, treatment plans requiring review, assessments, authorization limits, and supervisor signatures.
AI-enabled practice operating systems can help draft and organize documentation, but the larger benefit comes from placing that assistance inside the operating workflow. The system should know which document is required, why it matters, and whether the encounter is ready to become a claim.
Clean Claims Start Before Submission
Traditional billing processes often discover problems after a payer rejects or denies the claim. The Patient-to-Payment Cycle moves that intelligence earlier. Before submission, the system can check eligibility, authorization, provider enrollment, required documentation, procedure codes, and modifiers, place of service, diagnosis compatibility, duplicates, and filing deadlines.
After submission, the same workflow should monitor acknowledgments, remittances, rejections, denials, underpayments, and stalled claims. When intervention is required, the system should explain the problem, recommend the next action, and route it to the right person.
People Should Manage Exceptions
Reducing administrative work does not require removing people from the process. It requires using their judgment where it has the most value. Routine, high-confidence actions can occur automatically. Unusual situations can be prepared for one-click approval. Complex clinical, payer, or credentialing issues can be escalated with the relevant information already assembled.
This changes the daily question from what work is waiting to what requires human judgment. Practice leaders gain a clearer view of blocked revenue, repeated workflow failures, provider bottlenecks, and the percentage of appointments reaching payment without billing intervention.
The System Improves Through Use
Every completed cycle produces useful operational knowledge. The platform learns which payer rules matter, which documentation gaps delay claims, which rejection patterns recur, and which actions lead to payment. Over time, work can move from manual handling to recommended action and then to automation.
That accumulated payer and workflow knowledge is more durable than any individual AI feature. It reflects the real behavior of behavioral health practices, providers, patients, claims, and insurance plans inside one connected process.
A Simpler Standard for Practice Technology
Behavioral health practices operating system should expect their technology to do more than store records and present task lists. The platform should actively move work forward, complete routine actions, and bring people into the process when their attention is genuinely needed.
The Patient-to-Payment Cycle gives DENmaar a clear standard for every product decision: does this capability help a patient reach care and help the practice collect the revenue earned for that care? When the answer is yes, it belongs in the core operating system.
DENmaar connects patient access, clinical workflow, insurance intelligence, and revenue cycle operations in one behavioral health platform.
Learn how DENmaar can help your practice manage the complete Patient-to-Payment Cycle.
Frequently Asked Questions
What is an operating model for behavioral health?
An operating model for behavioral health connects patient access, clinical care, insurance, billing, claims, and payment in one workflow.
What is the Patient-to-Payment Cycle?
It connects the patient’s first contact with scheduling, care, documentation, billing, claims, and collected revenue.
How can AI improve behavioral health workflows?
AI can automate routine work, identify missing information, organize tasks, and help staff focus on exceptions requiring human judgment.
Why should claims be checked before submission?
Pre-submission checks can identify eligibility, authorization, documentation, coding, and other issues before they cause claim delays or denials.
What should behavioral health technology connect?
It should connect patient access, scheduling, clinical documentation, insurance, billing, claims, credentialing, and revenue cycle operations.
Our Partners






Ready to get started?
Feel free to reach out if you have any questions.
