

- Therapy and medication management
- IOP, PHP, and SUD treatment programs
- Case management, community support, and residential services
DENmaar Revenue Cycle Intelligence
Claims Copilot ™
Stop Chasing Claims.
Start Preventing Problems.
Claims Copilot is DENmaar’s behavioral health revenue cycle solution
designed to help practices prevent claim issues before submission, reduce
aging, accelerate reimbursement, and improve operational performance.

Pre-Submission Claim Readiness

Payer Lifecycle Monitoring

Aging & Collections Visibility
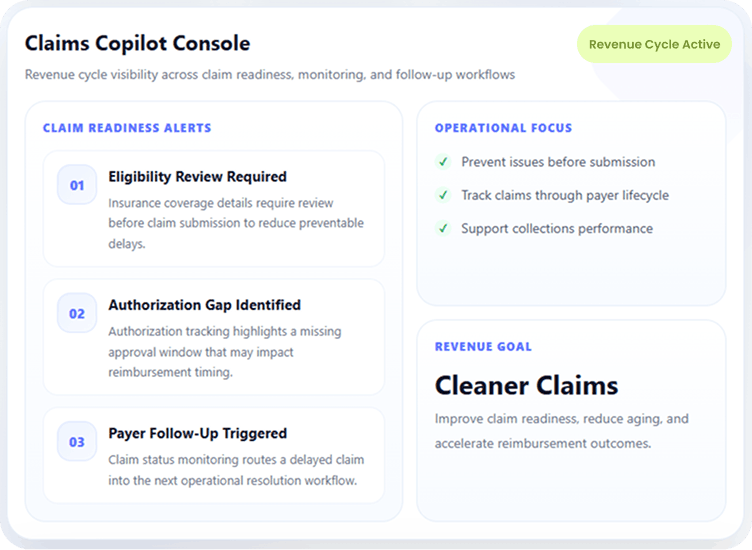
Pre-Submission Readiness
Catch eligibility, authorization, payer, and documentation issues before claims go out.
Lifecycle Claim Monitoring
Track claims after submission with rejection management, status visibility, and aging oversight.
Operational Performance
Support clean claim performance, reduce aged claims, and improve collections visibility.
Behavioral Health Focused
Designed for therapy, medication management, SUD, IOP/PHP, community support, and more.
Built for Behavioral Health
Designed for Behavioral Health
Revenue Cycle Workflows
Whether your organization provides therapy, medication management, IOP,
PHP, SUD treatment, case management, community support, or residential
services, Claims Copilot is built around the operational and reimbursement
realities of behavioral health.

Behavioral health support areas
Claims Copilot is positioned to support behavioral health organizations that need stronger claim readiness, reimbursement visibility, and operational follow-up across complex service lines.
Prevent Problems Before Claims Are Submitted
Address Revenue Cycle Breakdowns
Before They Turn Into Denials or Delays
Most claim problems begin long before a claim is submitted. Claims Copilot helps practices identify and
resolve those issues earlier so reimbursement performance is not undermined later.

Verify Insurance Eligibility
Confirm insurance coverage details early to reduce preventable reimbursement delays and billing confusion.

Review Insurance Information & ID Cards
Validate insurance information and supporting details so claims are built on more accurate payer data.

Track Authorizations
Monitor authorization requirements and approval status to reduce avoidable denials tied to missing coverage approvals.

Monitor Provider Credentialing Requirements
Support awareness of credentialing-related payer requirements that can affect billing and reimbursement workflows.

Identify Claim Issues Before Submission
Catch missing information, workflow gaps, and other claim barriers before the claim enters the payer lifecycle.

Improve Documentation-to-Billing Alignment
Route messages and requests to the appropriate team, department, or follow-up queue.
How Claims Copilot Works
A continuous workflow built to
support prevention, monitoring, and resolution.
Claims Copilot doesn’t stop at submission. It supports the operational work needed before the claim goes out, then continues
tracking activity through the payer lifecycle to help teams reduce delays, aging, and reimbursement bottlenecks.
1
Review claim readiness before submission
Insurance, eligibility, authorization, and workflow details are reviewed to identify claim risks before they become downstream reimbursement problems.
2
Submit claims and monitor payer activity
Once claims are submitted, Claims Copilot supports visibility into rejections, claim status, aging, and other signals that indicate a claim may require action.
3
Route follow-up through the right workflow
Operational tasks can be prioritized based on the issue—whether the next step involves internal follow-up, claim correction, payer research, or payment posting support.
From prevention to reimbursement performance.
Claims Copilot is designed to help organizations manage the full payer journey—not just claim submission. The result is a more proactive revenue cycle process with clearer visibility and fewer avoidable surprises.

Before submission:
improve readiness across insurance, authorizations, and documentation alignment

After submission:
monitor claim status, rejections, denial patterns, and aging across the payer lifecycle.

Operationally:
help teams reduce aging, recover delayed payments, and improve turnaround performance.
Monitor Claims Through the Entire Payer Lifecycle
Submitting claims is only the beginning.
Claims Copilot continuously tracks claim progress and supports the workflows needed to identify
reimbursement issues, respond to payer friction, and keep claims moving toward payment.

Claim Submission & Rejection Visibility
Support clean electronic claim submission while maintaining visibility into rejections and claim issues that need attention after submission.
- Electronic claim submission
- Rejection management support
- Visibility into claim readiness breakdowns

Status Monitoring & Aging Analysis
Track claims after submission to identify delays, payer inactivity, unresolved statuses, and aging trends that can impact collections.
- Claim status monitoring
- Aging analysis and prioritization
- Operational follow-up workflow visibility

Denials, Follow-Up & Payment Support
Improve follow-through on denied or delayed claims by supporting structured next steps across payer follow-up, resolution activity, and payment posting workflows.
- Denial tracking
- Follow-up workflow support
- Payment posting support
Reduce Aging and Improve Collections
Give your organization earlier visibility, better follow-through, and fewer preventable delays.
Many behavioral health organizations struggle with growing accounts receivable because claim issues are discovered too late. Claims Copilot helps teams stay ahead of the work required to keep reimbursement moving.

Reduce aged claims
improve readiness across insurance, authorizations, and documentation alignment.

Recover delayed payments
Identify unresolved payer issues sooner and reduce the amount of time claims spend waiting without meaningful action.

Improve turnaround and clean claim performance
Support stronger revenue cycle performance by reducing preventable breakdowns before and after submission.
A Partnership Approach
Successful revenue cycle management requires operational collaboration.
Many behavioral health organizations struggle with growing accounts receivable because claim issues are discovered too late. Claims Copilot helps teams stay ahead of the work required to keep reimbursement moving.

Before submission:
improve readiness across insurance, authorizations, and documentation alignment.

After submission:
monitor claim status, rejections, denial patterns, and aging across the payer lifecycle.

Operationally:
help teams reduce aging, recover delayed payments, and improve turnaround performance.
Included With DENmaar
Claims Copilot is part of the DENmaar
Behavioral Productivity Platform.
When DENmaar manages your insurance billing, your organization also gains access to the broader operational and clinical
platform that supports scheduling, documentation, reporting, and patient management workflows.

Behavioral Health EHR
Clinical and operational workflows designed around behavioral health documentation and care delivery.

Scheduling
Integrated scheduling workflows to support patient flow, operational visibility, and billing readiness.

Documentation Tools
Clinical notes, treatment plans, and documentation workflows that support stronger operational alignment.

AI-Assisted Notes
Support documentation efficiency while maintaining professional review and oversight workflows.

Treatment Plans
Behavioral health planning tools that connect care planning with documentation and operational workflows.

Clinical Workflows
Support multidisciplinary behavioral health processes with connected operational and clinical workflows.

Reporting
Visibility into productivity, claim performance, and operational trends across the platform.

Patient Management Tools
Connected workflows for patient registration, intake coordination, operational follow-up, and practice support.
Request an
AI Notes Trial
See how DENmaar AI Notes can help your clinicians reduce documentation time while improving
Request a demonstration or pilot program today.
Request Information
TESTIMONIALS
WHAT OUR CLIENTS SAY
On behalf of everyone at Meadowlark Counseling Services, I want to extend our sincere thanks for the continued improvements you and your team have made to the DENMaar EMR platform. We have been consistently impressed with both the functionality and user-friendly design of the system, which has made a meaningful difference in our day-to-day operations. The intuitive layout and ease of use have allowed our staff to spend less time navigating the system and more time focusing on client care. The regular updates and enhancements reflect your commitment to meeting the evolving needs of providers in the behavioral health and substance use treatment fields. We genuinely look forward to the new features introduced each month and appreciate how responsive the platform has been to the demands of clinical workflows. We have been so pleased with our experience that we’ve taken the opportunity to recommend DENMaar to other professionals in Pennsylvania who are working in the SUD field. Thank you again for your ongoing support and partnership. We are grateful to be working with a company that truly understands the needs of its users. KIndly, Becky Parks on behalf of the entire team at Meadowlark Counseling Services
I referred one of my colleagues Dr Aaron to you he is just starting g his psychology private practice and looking at where to start. I told him hands down you guys are the best billers and have a great EMR and team. He said he reached out just wanted to let you know!
FANTASTIC job keeping things rolling along with any and all of our billing concerns as well as responding to other issues which may well have been out of your wheelhouse. We are VERY grateful to have you and the crew in our corner.
I appreciate you all so much and DENmaar has been such a blessing Donna to our overall operations and success as an expanding company—allowing us to ultimately operate more efficiently, get our claims paid more consistently, ad stay on top of the critical credentialing piece, among other things. Teamwork does in fact, make the dream work. I’ll loop Chris/Isabella in on this message thread too, as I want All of your team to be aware of how much we appreciate our working relationship with DENmaar
Thank you for your diligence!! I appreciate it so much. Thank you Edwina…
Thank you so much Amy! I will be referring to DENmaar as often as I am asked about credentialing services.
Our Latest Blogs
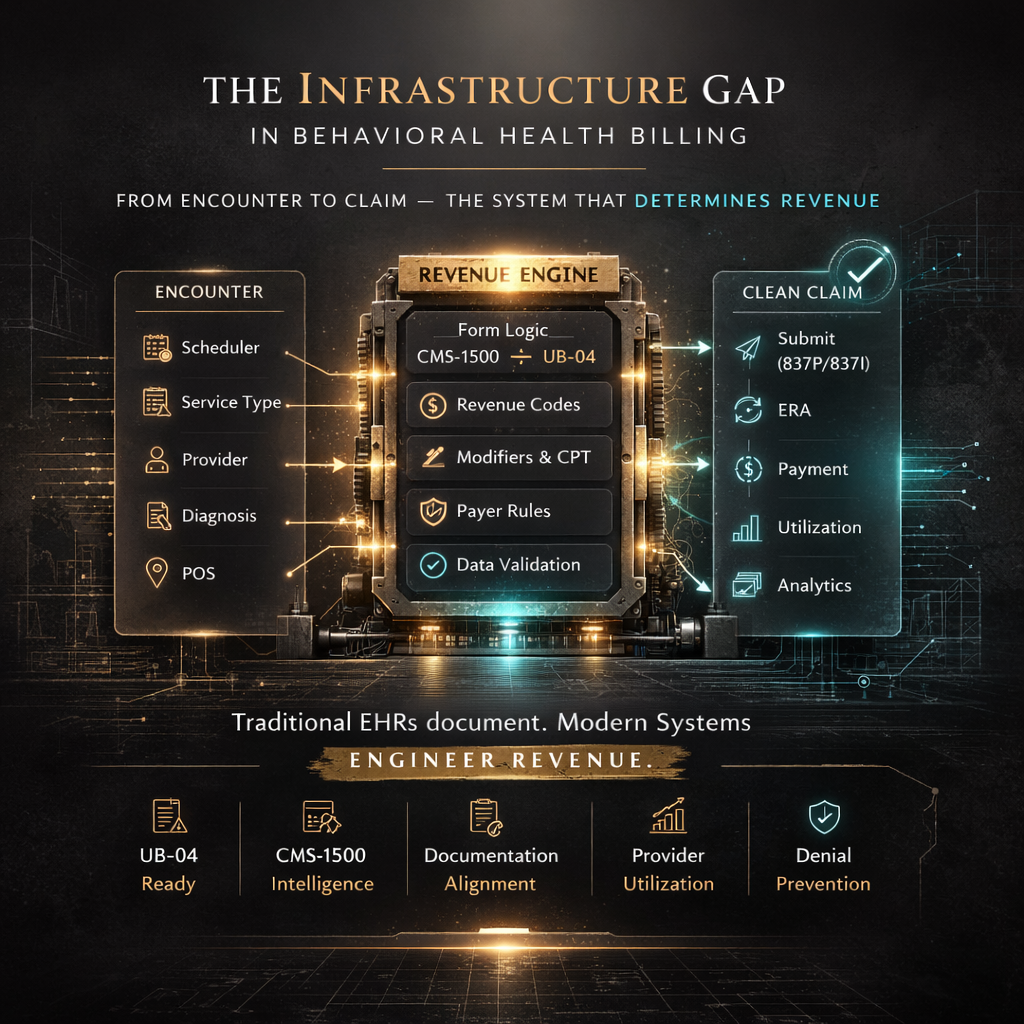
The Infrastructure Gap in Behavioral Health Billing
Why most EHR platforms were never designed for complex revenue
Behavioral health has a revenue problem and it isn’t payer rates.
It’s infrastructure.
Most EHR platforms were designed for documentation first, billing second. That model works for solo therapy practices submitting basic CMS-1500 claims. It breaks down the moment complexity enters the picture.
And complexity is now the rule, not the exception.
For many organizations, this structural gap is one of the reasons behavioral health practices lose 10–20% of insurance revenue without realizing it.
Where Systems Begin to Fail
As practices expand into:
- Intensive Outpatient Programs (IOP)
- Community Mental Health (CMHC) services
- ACT, PSR, and H2038 programs
- Multi-discipline care models
- Medicaid Managed Care carve-outs
They encounter a structural reality:
CMS-1500 logic alone is not enough.
UB-04 becomes necessary. Revenue codes become necessary. Type-of-Bill fields matter. Rendering vs. attending provider logic matters. Diagnosis pointers and modifiers are no longer optional details — they are claim survival requirements.
Yet most platforms treat these as add-ons, not core architecture.
That’s the gap.
Without strong behavioral health billing services and revenue cycle management infrastructure, these requirements create systemic claim friction.
The Encounter to Claim Disconnect
In many systems:
Scheduler → Note → Claim
are loosely connected.
But in complex billing environments, these must be unified.
At the encounter level, the system must already know:
- Whether the service maps to CMS-1500 or UB-04
- What revenue code is required
- What modifiers are payer-specific
- Which provider field populates where
- How diagnosis pointers align to CPT lines
- What place of service logic applies
If this logic is not embedded upstream, denial management becomes downstream chaos.
Strong behavioral health EHR and mental health EHR software must align documentation, billing rules, and payer requirements before a claim is generated.
Clean Claims Are an Architectural Outcome
High clean-claim rates are not achieved by working harder.
They are achieved by designing systems where:
- Documentation aligns with billing requirements
- Service types control form type automatically
- Revenue codes are required when necessary
- Payer rule tables are embedded
- Eligibility carve-outs are detected before submission
This approach reflects the concept of claims hygiene in behavioral health billing, where payer rules and documentation logic are enforced upstream.
When infrastructure is correct, denials decline structurally.
When infrastructure is weak, billing teams become firefighters.
Utilization Is Revenue, Not Just Scheduling
A second infrastructure blind spot is provider utilization.
Behavioral health revenue is directly tied to:
- Delivered units
- Authorization alignment
- Cancellation management
- Provider productivity
If your system cannot measure utilization accurately, it cannot optimize revenue.
In percentage-based revenue models, this alignment becomes even more critical.
Structured clinical documentation, including AI-assisted progress notes for behavioral health, can also support payer-aligned billing accuracy and improve clean claims performance.
The Shift That’s Coming
The era of disconnected tools is fading.
Documentation, billing logic, and utilization reporting must converge into a single revenue-intelligent engine.
Behavioral health is becoming more complex, not less. Medicaid programs are expanding. Multi-discipline care models are growing. Compliance scrutiny is increasing.
Infrastructure must mature accordingly.
The practices that win over the next decade will not simply document well.
They will design their revenue systems deliberately.
Organizations building scalable behavioral health infrastructure increasingly rely on integrated systems such as DENmaar’s behavioral health platform.
No hype.
No promises.
Just structural clarity.
Frequently Asked Questions
Why do many behavioral health EHR systems struggle with complex billing?
Many EHR platforms were originally designed for documentation rather than revenue cycle management. When organizations add services like IOP, CMHC programs, or Medicaid-based care, the billing complexity exceeds the system’s original architecture.
What is the difference between CMS-1500 and UB-04 billing in behavioral health?
CMS-1500 forms are typically used for professional services such as therapy and psychiatry. UB-04 forms are used for institutional services such as IOP or facility-based care where revenue codes and type-of-bill fields are required.
What is behavioral health claims hygiene?
Claims hygiene refers to structuring documentation, payer logic, eligibility verification, and billing rules so that claims are correct before submission, reducing denials and improving clean claim rates.
Why is revenue cycle infrastructure important for Medicaid behavioral health billing?
Medicaid behavioral health programs often include carve-outs, unique modifiers, HCPCS codes, and authorization rules. Without integrated infrastructure inside the EHR and billing workflow, practices experience denials, delays, and revenue leakage.
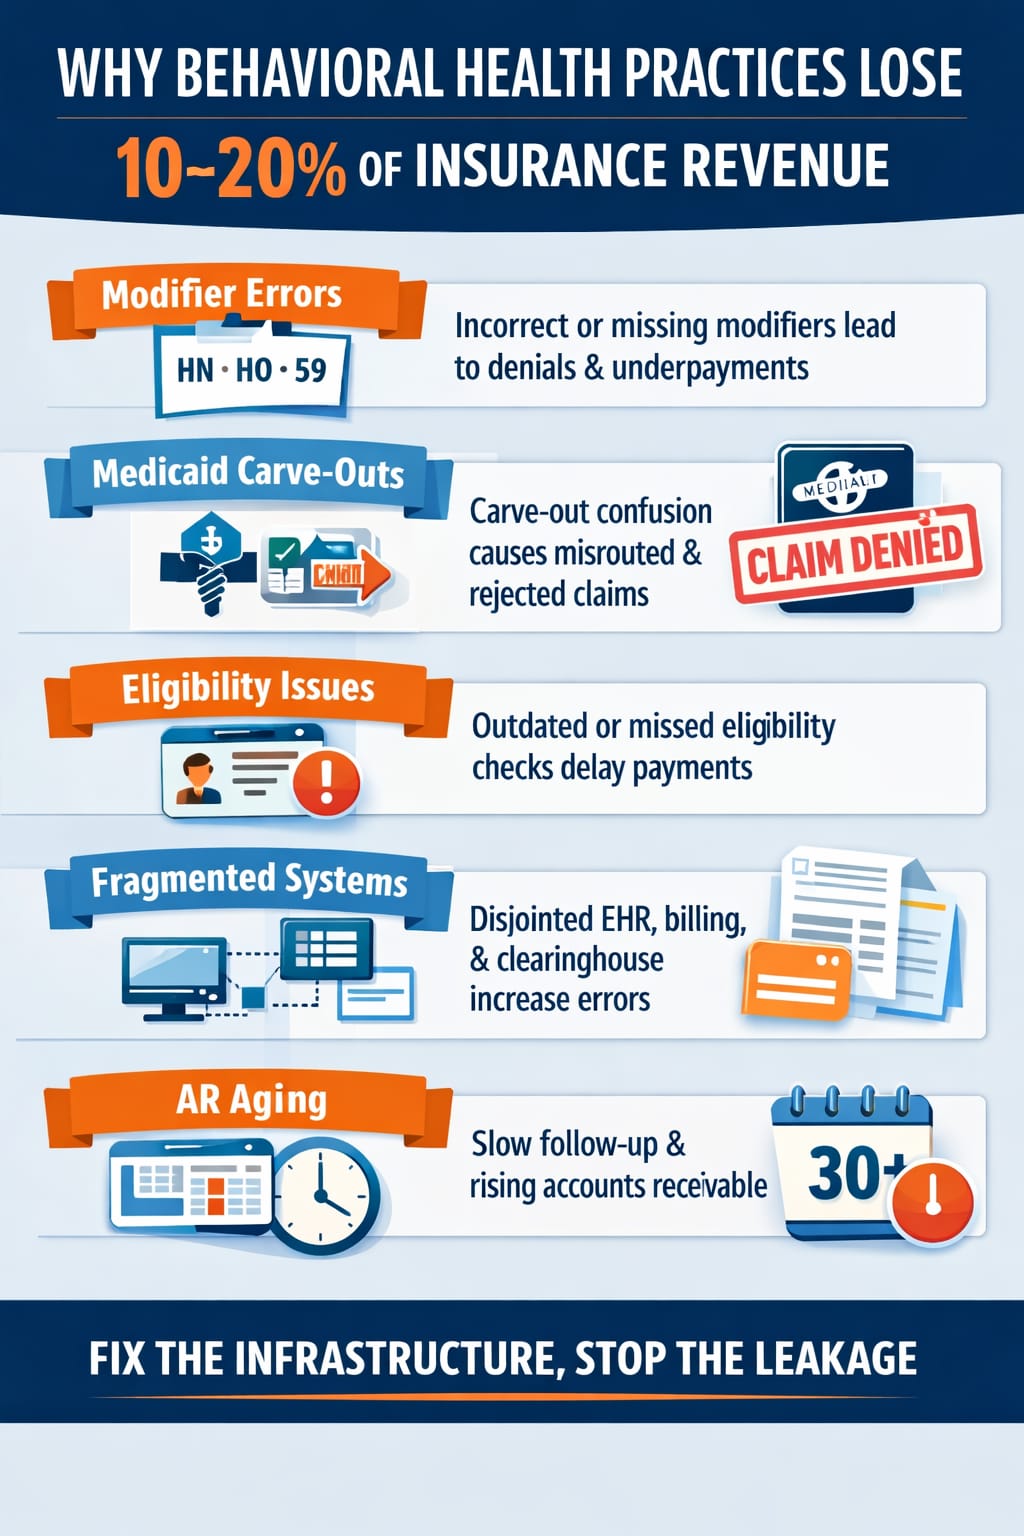
Why Behavioral Health Practices Lose 10 to 20 Percent of Insurance Revenue Without Realizing It
Most behavioral health practices believe their billing is “fine.”
Claims are going out. Payments are coming in. Denials do not look catastrophic.
But here is the uncomfortable reality:
Many practices quietly lose 10 to 20 percent of their insurance revenue, not because of fraud, incompetence, or bad providers, but because of structural claims friction.
Let’s break down where it actually leaks.
For a deeper system-level explanation, see claims hygiene in behavioral health billing.
1. Modifier Misalignment
Behavioral health is modifier heavy:
- HN / HO / HQ / HR
- 59 vs XE
- Facility vs professional billing logic
- State specific Medicaid rules
If modifier logic is not system enforced before submission, denials increase or worse, underpayments go unnoticed.
Small errors multiplied across thousands of Medicaid claims behavioral health submissions equal real revenue loss.
Without integrated behavioral health billing services and structured validation inside the EHR, modifier drift becomes systemic.
2. Medicaid Carve-Out Confusion
Behavioral health is often carved out from:
- Standard MCOs
- Commercial BCBS products
- State Medicaid networks
If eligibility verification does not detect carve-outs correctly, claims get routed incorrectly or denied after 30 or more days.
That is not a provider problem. That is infrastructure failure.
Strong behavioral health EHR and mental health EHR software systems must detect payer carve-outs before claims are generated.
3. Eligibility Gaps
Manual eligibility checks miss:
- Coverage changes
- Terminations
- Plan transitions
- Secondary payer coordination
A single eligibility miss can delay payment 45 to 60 days.
Multiply that across 15 to 20 providers and AR silently stretches.
Effective RCM for behavioral health requires real time eligibility logic built directly into the workflow, not spreadsheet tracking.
4. Fragmented Tools
Most practices operate with:
- Standalone EHR
- External biller
- Clearinghouse
- Manual tracking spreadsheets
- Email based follow up
Every handoff increases error probability.
Disconnected systems create invisible friction.
Integrated infrastructure, where EHR, documentation, and revenue cycle management operate together, reduces that friction significantly.
See how a technology plus services model works in practice
5. AR Aging Without Automation
If 30 day AR is not aggressively monitored and worked:
Revenue decays.
Most billing teams are reactive.
Top performing behavioral health revenue cycle management systems are proactive.
When claims infrastructure is engineered upstream, including structured documentation such as AI powered progress notes that align with payer rules, AR stabilizes and clean claims behavioral health performance improves.
The Difference Between Billing and Infrastructure
Billing is a task.
Infrastructure is a system that:
- Scrubs claims before submission
- Automates modifier logic
- Detects carve-outs
- Tracks AR aging in real time
- Reduces manual intervention
- Aligns compensation with collected revenue
When claims infrastructure is integrated directly into the EHR and RCM process, revenue leakage drops dramatically.
In our experience, many practices see 10 to 20 percent improvement in insurance revenue simply by eliminating friction.
Not by seeing more patients.
Not by raising rates.
By fixing structure.
Learn more about building infrastructure instead of chasing denials at DENmaar
Final Thought
If you do not measure:
- Clean claim rate
- Rejection percentage
- Denial percentage
- 0 to 30 day AR
- Cost per claim
You are not optimizing revenue.
You are hoping.
Hope is not a revenue strategy.
Frequently Asked Questions
Why do behavioral health practices lose insurance revenue?
Most revenue loss comes from modifier misalignment, Medicaid carve-out errors, eligibility gaps, and fragmented billing infrastructure rather than outright denials.
How much revenue leakage is normal in behavioral health billing?
Many practices unknowingly lose 10 to 20 percent of potential insurance revenue due to preventable structural issues in their EHR and revenue cycle workflow.
Does better billing staff fix revenue leakage?
Not alone. Revenue optimization requires system-level infrastructure that enforces payer rules, authorization logic, and clean claims standards before submission.
How can practices improve Medicaid behavioral health reimbursement?
By integrating eligibility detection, modifier enforcement, authorization tracking, and real time AR monitoring directly into their behavioral health EHR and RCM workflow.
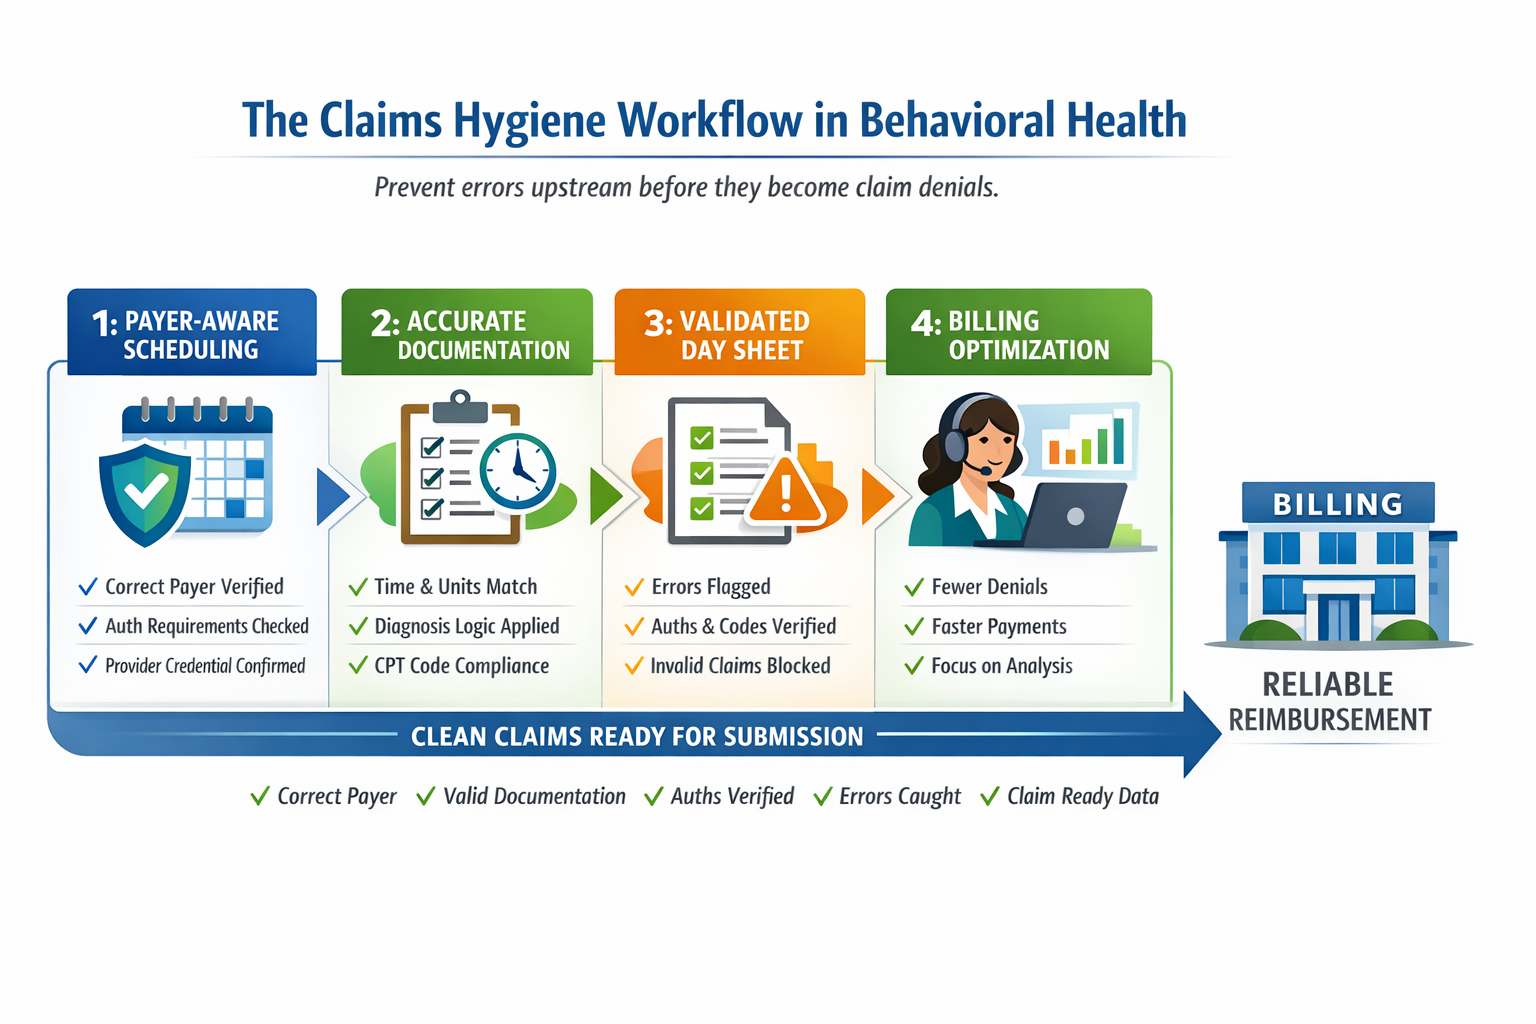
What “Claims Hygiene” Really Means in Behavioral Health
And Why Most Practices Are Fixing It Too Late
Most behavioral health practices think claim problems start in billing.
They don’t.
By the time a claim reaches a billing team, the outcome is already largely determined. Denials, rejections, underpayments are usually symptoms of upstream breakdowns that occurred days or weeks earlier inside the EHR.
We call this claims hygiene.
And if it is not engineered into your system, no amount of billing follow-up will fully fix it.
For a deeper breakdown of structured prevention, see claims hygiene in behavioral health billing.
Claims Hygiene Defined
Claims hygiene is the condition where every step before claim submission is structurally aligned to produce a payable claim by default.
That includes:
- Correct payer identification, especially mental health carve-outs
- Authorization-aware scheduling
- Time and unit accurate documentation
- Diagnosis logic that matches the service performed
- Day sheet logic that enforces payer rules before release
When these elements are clean and coordinated, billing becomes simple.
When they are not, billing becomes damage control.
This is not just a billing workflow. It is behavioral health revenue cycle management designed upstream inside the EHR.
Where Claims Actually Break (Upstream, Not in Billing)
In behavioral health billing, especially in Medicaid billing behavioral health environments, claim failure usually originates in one of four places:
1. Scheduling Without Payer Logic
Appointments are booked without confirming:
- The correct mental health payer
- Whether the service requires authorization
- Whether the provider is credentialed for that payer or program
Once the visit happens, the financial risk is already locked in.
Without integrated provider credentialing and insurance credentialing services awareness, scheduling becomes financially blind.
2. Documentation That Is Clinically Fine but Billing Unsafe
Notes often fail not because they are poor clinically, but because:
- Time thresholds do not match billed units
- Services rendered do not align with diagnosis logic
- Required elements for specific CPT or HCPCS codes are missing
Billing teams cannot fix documentation that was never structured correctly.
This is where structured AI documentation for behavioral health, including AI powered progress notes, becomes critical. Documentation must be payer aware, not just clinically complete.
3. Day Sheets That Do Not Enforce Rules
The day sheet is the last gate before claim submission and in many systems, it is passive.
If a day sheet allows:
- Invalid unit counts
- Missing authorizations
- Diagnosis and code mismatches
Then the system is allowing bad claims to exist.
A strong behavioral health EHR and mental health EHR software platform should enforce payer logic before claims are generated
4. Billing Teams Forced Into Manual Recovery
This is where most practices focus, but it is already too late.
At this stage, billing teams are:
- Correcting errors they did not create
- Appealing preventable denials
- Chasing missing information retroactively
This is not revenue cycle management. It is revenue triage.
True behavioral health billing services should prevent these breakdowns before submission.
Why “Clean Claims” Is the Wrong Goal
Many platforms advertise clean claim rates, but that metric is misleading.
A claim can be clean to a clearinghouse and still:
- Hit the wrong payer
- Violate MCO rules
- Fail authorization requirements
- Deny weeks later
True clean claims in behavioral health are payer true, service true, and rule true before submission ever happens.
This is especially critical in Medicaid claims behavioral health, psychiatry billing Medicaid, and substance use treatment billing environments where CMS 1500 versus UB 04 differences and managed care carve-outs matter.
Why Scaling Makes This Worse Fast
At 1 to 2 providers, errors are survivable.
At 10 or more providers:
- Small inconsistencies become systemic revenue loss
- Training breaks down
- Manual checks do not scale
- Billing headcount grows without fixing root causes
This is why many practices hit a ceiling where revenue plateaus despite growing volume.
Scaling requires system enforced behavioral health compliance, not manual memory.
What Real Claims Hygiene Looks Like
In a hygienic system:
- Insurance verification identifies mental health carve-outs automatically
- Scheduling is constrained by authorization and credentialing reality
- Documentation enforces time, units, and service logic
- Day sheets block invalid claims by design
- Billing teams focus on optimization, not cleanup
When this is in place, practices typically see:
- Fewer rejections and denials
- Faster payment cycles
- Lower billing staff burnout
- 10 to 20 percent improvement in realized insurance revenue without adding patients
This is the difference between submitting claims and building a revenue safe behavioral health system.
The Core Insight
Claims hygiene is not a billing function.
It is a system design problem.
If your EHR allows bad data to flow freely, billing will always be reactive.
If your system enforces payer aware logic upstream, billing becomes predictable and scalable.
Learn more about system level prevention at DENmaar.
Final Thought
Most practices do not need better billers.
They need fewer preventable mistakes.
Claims hygiene is not something you fix after the fact.
It is something you engineer into the workflow.
That is the difference between submitting claims and building a revenue safe system.
Frequently Asked Questions
What is claims hygiene in behavioral health billing?
Claims hygiene is the upstream enforcement of payer logic, authorization requirements, diagnosis alignment, and documentation accuracy before claims are submitted.
Why do Medicaid behavioral health claims deny so often?
Most denials stem from incorrect payer identification, missing authorizations, credentialing mismatches, or documentation errors created before billing ever sees the claim.
Can billing teams fix documentation errors?
No. Billing teams can correct coding or submission issues, but they cannot retroactively fix structurally flawed documentation.
How does an EHR improve clean claim rates?
A behavioral health EHR that enforces payer aware logic, authorization validation, and structured documentation reduces preventable denials before submission.
Our Partners






Ready to get started?
Feel free to reach out if you have any questions.
