

- Session transcription
- DAP, SOAP, and BIRP progress notes
- Psychiatry and medication-management documentation
- Biopsychosocial assessments
- Individualized treatment plans
- Measurable goals and objectives
- Group and multidisciplinary documentation
- Integration of clinical assessments and outcome measures
- Continuity between the treatment plan and subsequent notes
AI Notes for Behavioral Health
AI Built Into the
Work of the Practice.
From the first patient call through documentation, claims, and payment.
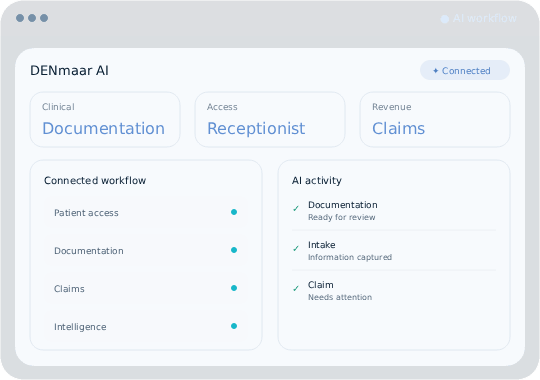
DENmaar applies AI across the connected workflow of a behavioral health practice—not only to generate progress notes.
Because DENmaar brings the EHR, scheduling, billing, credentialing, and operational support into one platform, AI can help move work forward across the entire organization.
One platform. One connected workflow. AI where the work actually happens.

Behavioral Health Focused

Clinical Accuracy & Oversight

Billing Workflow Ready
AI Notes
More Than an AI Note Generator
Most healthcare AI products solve one isolated task. They may transcribe a session, generate a note, answer a call, or analyze a claim—but the practice is still responsible for connecting those tools.
DENmaar takes a different approach.
We are building AI directly into the clinical, administrative, and financial workflows already used by the practice.
Information collected during intake can support documentation. Documentation can help prepare the claim. Claim information can guide billing follow-up. Operational data can help leadership see where work is becoming delayed.
The result is not simply more AI features. It is a more connected practice.
How DENmaar Uses AI
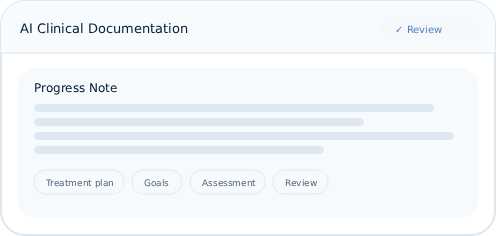
AI Clinical Documentation
Create behavioral health documentation using information already available within the patient record.
Providers remain in control. AI-generated content can be reviewed, edited, and approved by the clinician before it becomes part of the signed record.
How DENmaar Uses AI
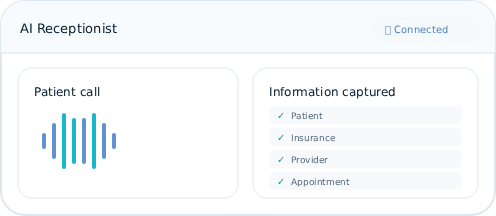
AI Receptionist
Respond to patients and prospective patients even when staff members are unavailable.
The DENmaar AI Receptionist is being designed around the real intake and scheduling needs of behavioral health organizations.
- Immediate call response
- New-patient information collection
- Appointment requests
- Rescheduling requests
- Common practice questions
- Insurance-information collection
- Provider and location routing
- After-hours coverage
- Call summaries and recommended follow-up
Because the AI Receptionist is connected to the DENmaar platform, the information it collects can become part of the practice workflow instead of remaining inside a separate answering service.
How DENmaar Uses AI
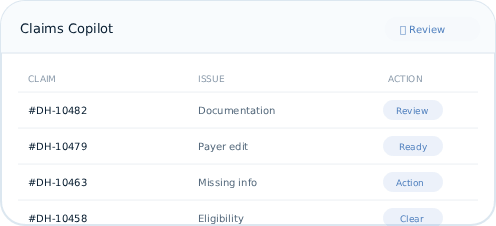
Claims Copilot
Help staff identify potential claim problems before they become lost revenue.
Claims Copilot brings AI and operational intelligence into the revenue-cycle workflow. It is designed to help billing teams understand what needs attention, why it needs attention, and what should happen next.
- Reviewing claims for missing or inconsistent information
- Identifying documentation and billing dependencies
- Highlighting claims that require follow-up
- Organizing work by urgency and financial impact
- Supporting denial and rejection analysis
- Recommending the next action
- Surfacing recurring payer or workflow problems
- Helping prevent avoidable delays before submission
Claims Copilot does not replace billing judgment. It gives the billing team better information and a clearer path through the work.
How DENmaar Uses AI
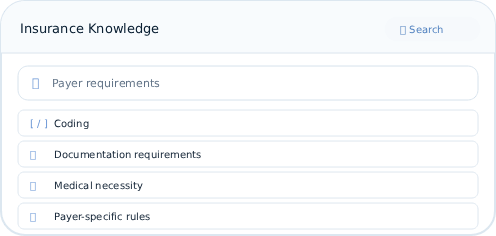
Insurance Knowledge
Turn years of behavioral health billing experience into accessible guidance.
Insurance requirements change constantly and often vary by payer, plan, state, provider type, and service. DENmaar is developing an expanding insurance knowledge resource informed by real behavioral health billing situations.
It can support questions involving:
- Coding
- Prior authorization
- Medical necessity
- Documentation requirements
- Claim resolution
- Credentialing
- Telehealth requirements
- Payer-specific rules
- Billing best practices
Instead of leaving practices to search scattered payer manuals or depend on disconnected information, DENmaar brings insurance knowledge closer to the workflow where decisions are made.
How DENmaar Uses AI
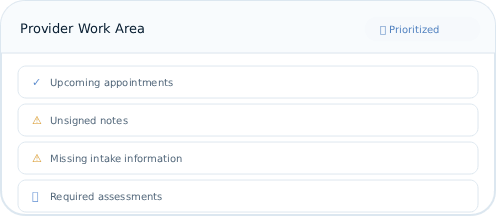
Intelligent Provider Workflow
Help every provider understand what requires attention next.
DENmaar’s Provider Work Area is being developed to organize clinical and administrative responsibilities into a single, prioritized view.
It will help providers identify:
- Upcoming appointments
- Missing intake information
- Eligibility or insurance concerns
- Incomplete documentation
- Unsigned notes
- Required assessments
- Treatment-plan updates
- Supervisor review requirements
- Other actions that could delay care or billing
The goal is simple: providers should not have to search through multiple screens to discover what they need to do.
How DENmaar Uses AI
Practice and Revenue Intelligence
Give leadership a clearer view of how the organization is operating.
By bringing scheduling, clinical documentation, provider activity, claims, and collections together, DENmaar can help practice leaders identify:
- Provider utilization
- Unfinished clinical work
- Workflow bottlenecks
- Claims waiting on documentation
- Recurring insurance problems
- Revenue-cycle exceptions
- Operational trends requiring attention
AI becomes most valuable when it helps the organization recognize problems earlier and take action before those problems affect patients, providers, or revenue.
Connected Patient Journey
One Patient Journey.
One Connected System.
The value of DENmaar’s AI is not limited to any single feature.
ONE CONNECTED WORKFLOW
AI working across the practice, from first contact through revenue-cycle operations.
01
PATIENT ACCESS
A prospective patient contacts the practice.
02
AI RECEPTIONIST
The AI Receptionist collects information and helps move the request into the appropriate scheduling or follow-up workflow.
03
INTAKE
The patient completes registration, insurance information, and assessments.
04
DOCUMENTATION
The provider uses those records and the session information to prepare clinical documentation.
05
BILLING READINESS
The completed documentation supports claim creation and billing readiness.
06
CLAIMS COPILOT
Claims Copilot helps identify exceptions and directs the billing team toward the next action.
07
PRACTICE INTELLIGENCE
Practice leadership can see where clinical, administrative, or financial work is becoming delayed.
THE CONNECTED OUTCOME
That is AI working across the practice—not another application working by itself.
Practice & Revenue Intelligence
AI That Helps the Organization
See What's Next
Connected data gives DENmaar more context about where work is happening, where it is delayed, and where
attention can have the greatest operational impact.
Prioritize Work
Surface the tasks and exceptions that need attention instead of making staff hunt for them.
Find Bottlenecks
Identify recurring workflow problems across clinical, administrative, and revenue-cycle operations.
Act Earlier
Recognize patterns before unfinished work becomes a patient-access, billing, or revenue problem.
Support Providers
Give clinicians a clearer view of documentation and administrative responsibilities.
Keep Humans in Control
AI assists the work while clinicians and staff retain responsibility for decisions.
Connect the Workflow
Use information already present in the DENmaar platform rather than recreating it in another tool.
Behavioral Healthcare
Designed for Behavioral Healthcare
DENmaar’s AI capabilities are built around the needs of behavioral health organizations, including:
Therapy
Psychiatry
Substance use disorder treatment
Group services
Multidisciplinary care
Multi-provider and multi-location practices
AI assists the work, but clinicians and staff retain responsibility for reviewing information and making clinical, administrative, and billing decisions.
DENmaar AI
Built Today. Expanding Continuously.
DENmaar is introducing AI carefully across the platform. Some capabilities are available today, while others are in development or being expanded through controlled pilots.
During a demonstration, we will show you what is currently available, explain what is being developed, and evaluate which DENmaar workflows fit the needs of your organization.
No inflated promises. No disconnected AI tools. A practical path toward a more intelligent behavioral health practice.
Available today
Controlled pilots
Expanding continuously
Request an
AI Notes Trial
See how DENmaar AI Notes can help your clinicians reduce documentation time while improving
Request a demonstration or pilot program today.
Request Information
TESTIMONIALS
WHAT OUR CLIENTS SAY
On behalf of everyone at Meadowlark Counseling Services, I want to extend our sincere thanks for the continued improvements you and your team have made to the DENMaar EMR platform. We have been consistently impressed with both the functionality and user-friendly design of the system, which has made a meaningful difference in our day-to-day operations. The intuitive layout and ease of use have allowed our staff to spend less time navigating the system and more time focusing on client care. The regular updates and enhancements reflect your commitment to meeting the evolving needs of providers in the behavioral health and substance use treatment fields. We genuinely look forward to the new features introduced each month and appreciate how responsive the platform has been to the demands of clinical workflows. We have been so pleased with our experience that we’ve taken the opportunity to recommend DENMaar to other professionals in Pennsylvania who are working in the SUD field. Thank you again for your ongoing support and partnership. We are grateful to be working with a company that truly understands the needs of its users. KIndly, Becky Parks on behalf of the entire team at Meadowlark Counseling Services
I referred one of my colleagues Dr Aaron to you he is just starting g his psychology private practice and looking at where to start. I told him hands down you guys are the best billers and have a great EMR and team. He said he reached out just wanted to let you know!
FANTASTIC job keeping things rolling along with any and all of our billing concerns as well as responding to other issues which may well have been out of your wheelhouse. We are VERY grateful to have you and the crew in our corner.
I appreciate you all so much and DENmaar has been such a blessing Donna to our overall operations and success as an expanding company—allowing us to ultimately operate more efficiently, get our claims paid more consistently, ad stay on top of the critical credentialing piece, among other things. Teamwork does in fact, make the dream work. I’ll loop Chris/Isabella in on this message thread too, as I want All of your team to be aware of how much we appreciate our working relationship with DENmaar
Thank you for your diligence!! I appreciate it so much. Thank you Edwina…
Thank you so much Amy! I will be referring to DENmaar as often as I am asked about credentialing services.
Our Latest Blogs
Why Most Behavioral Health EHRs Fail at Billing And What a Billing-Optimized System Actually Looks Like
Behavioral health practices often assume billing problems come down to staff performance. Claims get rejected, payments are delayed, and revenue fluctuates unpredictably. The typical conclusion is that the billing team needs better training or more oversight.
In reality, the problem usually starts much earlier in the system architecture.
Most behavioral health EHRs were never designed to support efficient behavioral health revenue cycle management. Billing was added later as an auxiliary feature rather than built into the clinical workflow itself. This structural issue creates ongoing problems that practices attempt to solve with more staff, more manual review, and more time spent chasing claims.
The result is predictable: lost revenue, administrative friction, and frustrated providers.
Modern organizations increasingly rely on integrated platforms like behavioral health EHR and mental health practice management software designed to align clinical workflows with billing accuracy and Medicaid reimbursement requirements.
The Structural Problem With Most EHRs
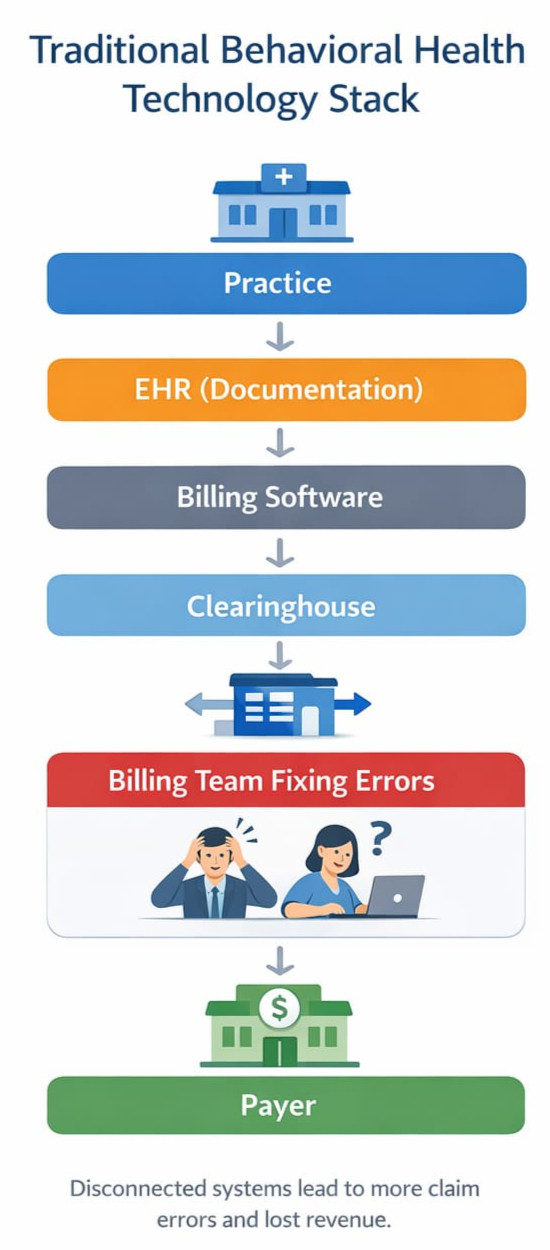
The traditional behavioral health technology stack looks something like this:
Practice → EHR → Billing Software → Clearinghouse → Billing Team
Each layer operates somewhat independently. Documentation is completed inside the EHR, then billing staff extract the information needed to generate claims. If documentation is incomplete, inconsistent, or coded incorrectly, the claim fails downstream.
This architecture introduces several common problems.
Documentation and Billing Are Disconnected
Clinical notes are written for clinical purposes, not claim validation. Important billing elements such as time requirements, service modifiers, or diagnosis linkage may not be captured correctly in the workflow.
Modern systems increasingly solve this problem through structured documentation and AI progress notes for behavioral health, ensuring that clinical documentation supports both care delivery and billing compliance.
Errors Are Discovered Too Late
In many systems, claim validation occurs only after the claim is generated and submitted. By that point, rejections or denials require additional staff intervention.
Eligibility and Payer Rules Are Separate From Clinical Workflow
Eligibility verification and payer specific requirements often live outside the EHR entirely. Front desk staff, clinicians, and billing teams operate with incomplete information about payer policies.
Claims Follow Up Becomes Labor Intensive
When problems occur, billing teams spend hours tracking down documentation errors, contacting payers, or correcting claims.
None of these problems are fundamentally about the billing staff.
They are system design problems.
The Real Cost of Fragmented Billing Systems
Behavioral health practices frequently underestimate how much revenue is lost through inefficient billing infrastructure.
Common revenue leakage points include:
- Incorrect or missing modifiers
- Mismatched documentation and CPT codes
- Eligibility verification failures
- Incorrect claim forms such as CMS-1500 vs UB-04
- Incomplete prior authorization tracking
- Delayed follow up on rejected claims
Across the industry, these issues typically reduce collected revenue by 10–20%.
Many organizations are unaware that behavioral health providers lose 10–20 percent of insurance revenue due to inefficiencies in billing workflows and claims management.
For many practices, that difference determines whether they are able to hire additional clinicians, expand services, or invest in better care infrastructure.
What a Billing-Optimized Behavioral Health EHR Looks Like
If billing performance depends on system architecture, the logical solution is to design the clinical system around revenue cycle integrity from the beginning.
A billing optimized behavioral health platform integrates several core elements directly into the workflow.
Documentation That Drives Coding
Clinical documentation should guide coding decisions rather than leaving coding entirely to billing staff. Structured note elements help ensure that required billing information such as time thresholds, service type, and diagnosis linkage is captured during the clinical encounter.
Integrated Eligibility and Payer Intelligence
Eligibility verification and payer rules should be visible within the system before services occur. This allows practices to confirm coverage, identify authorization requirements, and avoid preventable claim failures.
Pre Submission Claim Validation
Claims should be evaluated and scrubbed before submission to clearinghouses. Identifying errors upstream prevents the cycle of rejection, correction, and resubmission that slows revenue flow.
Maintaining strong claims hygiene in behavioral health billing is one of the most effective ways to improve clean claims rates and Medicaid reimbursement.
Continuous Claims Monitoring
Billing does not end at submission. Effective systems monitor claim status, identify payer responses, and intervene when issues arise.
Support for Multiple Billing Models
Behavioral health organizations increasingly operate across multiple service levels and billing structures. Systems must support both CMS-1500 professional claims and UB-04 institutional claims depending on the services provided.
Without this flexibility, practices are forced to maintain multiple disconnected systems.
Many organizations address this complexity through specialized behavioral health billing services and integrated revenue cycle management solutions.
Why This Matters for Behavioral Health
Behavioral health reimbursement is particularly complex compared with many other healthcare sectors.
Practices frequently operate across multiple disciplines including:
- Therapy
- Psychiatry
- Substance use disorder treatment
- Intensive outpatient programs (IOP)
- Community based services
- Case management
Each service category introduces different coding requirements, payer rules, and claim forms.
If billing logic is not integrated directly into the clinical infrastructure, the administrative burden grows rapidly as practices expand.
This is one reason many behavioral health organizations struggle to scale.
The Future of Behavioral Health Infrastructure
Over time, behavioral health technology will move away from isolated software tools toward integrated operating systems for practices.
In this model, documentation, billing, credentialing, communication, and analytics are connected within a unified platform.
Clinical workflow generates structured data that feeds directly into revenue cycle processes. Claims validation occurs automatically before submission. Eligibility, authorizations, and payer rules are continuously integrated into the system.
Platforms like DENmaar EHR are built around this concept, combining behavioral health documentation, billing workflows, and revenue cycle management into a single system.
The result is a much more stable and predictable revenue cycle.
The Results of an Integrated Approach
When billing architecture is built directly into the platform, claim performance improves dramatically.
At DENmaar, for example, practices operating within an integrated clinical and revenue cycle system currently achieve:
- 98.1% clean claims
- 1.47% rejected claims
- 0.32% denied claims
Those numbers place performance within the top tier of healthcare revenue cycle outcomes.
More importantly, practices using integrated systems typically experience 10–20% increases in insurance revenue simply by reducing claim friction and administrative leakage.
The Takeaway
When billing problems arise, it is easy to assume the issue lies with the billing team.
In many cases, the real cause is the technology architecture supporting the revenue cycle.
Behavioral health practices that want to grow sustainably need systems designed around billing integrity from the start rather than systems where billing is an afterthought.
As behavioral health services continue to expand and payer requirements grow more complex, billing optimized infrastructure will increasingly define which organizations succeed.
And which ones continue struggling with the same avoidable claim problems.
Frequently Asked Questions
Why do most behavioral health EHR systems struggle with billing?
Many behavioral health EHR platforms were originally designed for clinical documentation rather than revenue cycle management. Because billing was added later, documentation workflows, payer rules, and claim validation are often disconnected.
What is behavioral health revenue cycle management?
Behavioral health revenue cycle management refers to the full process of managing insurance claims, eligibility verification, coding, billing, and reimbursement for mental health and substance use treatment services.
Why are clean claims important in behavioral health billing?
Clean claims are insurance claims submitted without errors or missing data. Strong claims hygiene improves approval rates, reduces denials, and accelerates Medicaid behavioral health reimbursement.
How can AI improve behavioral health documentation and billing?
AI tools can automate clinical documentation and generate structured progress notes that align with billing requirements. This helps clinicians reduce administrative work while improving billing accuracy.

Why Behavioral Health Needs a New Operating Model
Multidisciplinary Care, Dual Claim Systems, and the Rise of Claims Hygiene
Behavioral health is changing.
Over the past decade, the industry has expanded beyond traditional outpatient therapy into a much broader continuum of care. Today’s practices increasingly include multiple service lines:
- Outpatient therapy
- Psychiatry and medication management
- Substance use disorder (SUD) treatment
- Intensive outpatient programs (IOP)
- Partial hospitalization programs (PHP)
- Community-based services
- Residential programs such as ASAM 3.1
Yet the technology supporting many of these organizations still assumes a simple model: one provider, one discipline, one claim type.
That assumption no longer holds.
Modern behavioral health organizations require systems designed around multiple disciplines, multiple billing frameworks, and increasingly complex payer rules.
The practices that understand this shift are building something fundamentally different.
For many organizations, adopting a modern behavioral health EHR platform and integrated behavioral health revenue cycle management approach is the first step toward solving these challenges.
The Multidisciplinary Behavioral Health Organization
The most resilient behavioral health organizations today are not single-service clinics.
They are multidisciplinary systems of care.
A single organization might include:
- Licensed therapists
- Psychiatrists and psychiatric nurse practitioners
- SUD counselors
- Case managers
- Community support specialists
- Residential program staff
Each discipline introduces different documentation standards, payer expectations, and billing structures.
A therapy session may be billed as CPT 90837, while case management could use T1016, and an intensive outpatient day might involve a facility-based service with entirely different billing rules.
Trying to run this ecosystem on software designed only for therapy quickly creates friction.
This is where the distinction between professional claims and facility claims becomes critical.
Many organizations discover they are losing significant insurance revenue due to billing inefficiencies, something explored in detail in this analysis of how providers lose 10–20% of insurance revenue due to revenue cycle gaps.
CMS-1500 vs UB-04: Two Claim Worlds in Behavioral Health
Behavioral health providers often operate across two fundamentally different claim systems.
Understanding CMS 1500 vs UB 04 billing is essential for accurate Medicaid behavioral health reimbursement and clean claims.
CMS-1500 (Professional Claims)
Used for services delivered by individual clinicians such as:
- Therapy sessions
- Psychiatric evaluations
- Medication management
- Individual counseling
These claims are built around:
- CPT / HCPCS procedure codes
- Rendering provider information
- Service units and modifiers
This is the traditional model most EHRs support.
But it is only half the story.
UB-04 (Facility Claims)
Programs such as IOP, PHP, residential treatment, and some SUD services may require facility billing.
These claims rely on a completely different structure:
- Revenue codes
- Facility identifiers
- Program-level billing logic
- Episode-based service tracking
Many organizations running these services discover that their EHR cannot properly support UB-04 workflows.
As a result, staff often build manual workarounds, spreadsheets, and external billing processes.
The operational cost of this fragmentation is enormous.
This is why many providers adopt specialized behavioral health billing services designed for complex Medicaid and multi-program organizations.
The Hidden Problem: Claims Hygiene in Behavioral Health Billing
Even with the right claim format, most behavioral health revenue cycles struggle with something far more basic.
Data integrity.
We call this claims hygiene in behavioral health billing.
Claims hygiene refers to the accuracy and completeness of the information required to produce a clean claim:
- Correct insurance identification
- Accurate payer routing
- Valid provider credentials
- Proper service coding
- Diagnosis linkage
- Authorization verification
- Clean eligibility data
When these elements are wrong or incomplete, claims fail.
The result is familiar to many organizations:
- Rising denial rates
- Aging receivables
- Administrative overload
- Lost revenue
Improving claims hygiene is often the fastest way to increase revenue without seeing a single additional patient.
Where Most Behavioral Health Systems Fail
Many EHR platforms were originally designed for small outpatient therapy practices.
They assume a simple model:
One clinician
One note
One claim
But multidisciplinary behavioral health organizations operate in a very different reality.
They need systems capable of supporting:
- Multiple clinical disciplines
- CMS-1500 professional claims
- UB-04 facility claims
- Complex Medicaid program structures
- Integrated behavioral health revenue cycle management workflows
Without this architecture, billing becomes an afterthought rather than an integrated system.
Organizations increasingly turn to purpose-built platforms like DENmaar EHR, designed specifically for behavioral health compliance, Medicaid billing workflows, and multi-program organizations.
The Future: Integrated Behavioral Health Operating Systems
The next generation of behavioral health platforms will not separate clinical documentation from revenue cycle management.
Instead, they will treat documentation, scheduling, and billing as a single operational system.
This means:
- Services mapped to claim type (CMS-1500 or UB-04)
- Documentation structured to support billing requirements
- Eligibility and payer data captured early in the workflow
- Claims validated before submission
When this approach is implemented correctly, organizations see dramatic improvements:
- Higher clean claim rates
- Faster reimbursements
- Reduced administrative workload
- More predictable revenue
Modern platforms are also introducing AI progress notes for behavioral health, allowing clinicians to automate documentation while maintaining compliance with billing requirements.
A System Designed for the Real Behavioral Health Market
The behavioral health industry is not simple.
It spans therapy, psychiatry, substance use treatment, residential care, and community-based services.
Technology must reflect that complexity.
The organizations that thrive in the next decade will be those that build systems around three principles:
- Multidisciplinary care delivery
- Support for both CMS-1500 and UB-04 claim structures
- Operational discipline around claims hygiene
This is not just a billing strategy.
It is a new operating model for behavioral health.
Frequently Asked Questions
What is the difference between CMS-1500 and UB-04 in behavioral health billing?
CMS-1500 is used for professional claims submitted by individual providers such as therapists and psychiatrists. UB-04 is used for facility-based services like intensive outpatient programs, residential treatment, and hospital services.
Why is claims hygiene important in behavioral health revenue cycle management?
Claims hygiene ensures that all billing data such as insurance information, provider credentials, and service codes are accurate before submission. Strong claims hygiene improves clean claims rates, Medicaid reimbursement, and behavioral health revenue cycle performance.
What software do behavioral health organizations need?
Modern organizations require behavioral health EHR systems with integrated billing, Medicaid claims support, and AI documentation tools to manage multidisciplinary care and complex billing workflows.
How can AI help behavioral health documentation?
AI documentation tools can generate AI progress notes and clinical summaries, reducing clinician workload while ensuring notes meet compliance and billing requirements.
The Infrastructure Gap in Behavioral Health Billing
Why most EHR platforms were never designed for complex revenue
Behavioral health has a revenue problem and it isn’t payer rates.
It’s infrastructure.
Most EHR platforms were designed for documentation first, billing second. That model works for solo therapy practices submitting basic CMS-1500 claims. It breaks down the moment complexity enters the picture.
And complexity is now the rule, not the exception.
For many organizations, this structural gap is one of the reasons behavioral health practices lose 10–20% of insurance revenue without realizing it.
Where Systems Begin to Fail
As practices expand into:
- Intensive Outpatient Programs (IOP)
- Community Mental Health (CMHC) services
- ACT, PSR, and H2038 programs
- Multi-discipline care models
- Medicaid Managed Care carve-outs
They encounter a structural reality:
CMS-1500 logic alone is not enough.
UB-04 becomes necessary. Revenue codes become necessary. Type-of-Bill fields matter. Rendering vs. attending provider logic matters. Diagnosis pointers and modifiers are no longer optional details — they are claim survival requirements.
Yet most platforms treat these as add-ons, not core architecture.
That’s the gap.
Without strong behavioral health billing services and revenue cycle management infrastructure, these requirements create systemic claim friction.
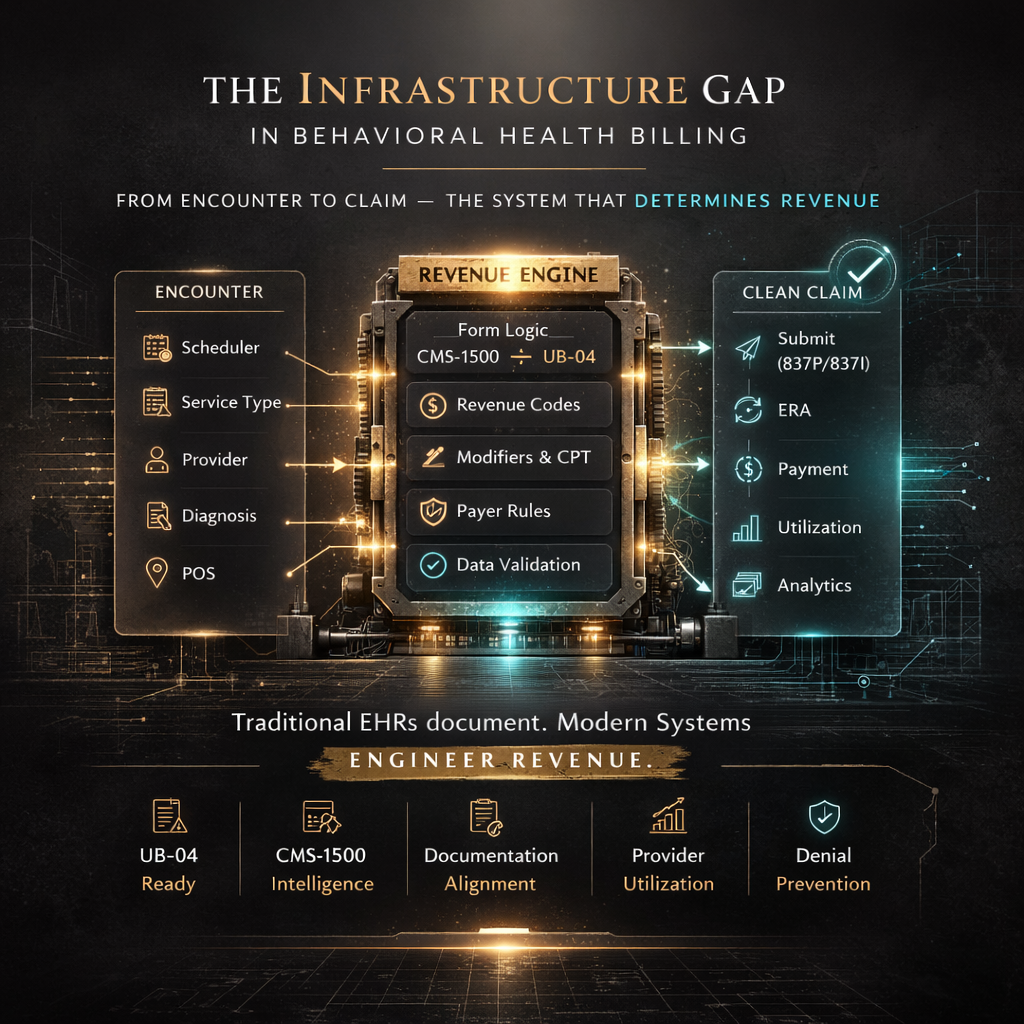
The Encounter to Claim Disconnect
In many systems:
Scheduler → Note → Claim
are loosely connected.
But in complex billing environments, these must be unified.
At the encounter level, the system must already know:
- Whether the service maps to CMS-1500 or UB-04
- What revenue code is required
- What modifiers are payer-specific
- Which provider field populates where
- How diagnosis pointers align to CPT lines
- What place of service logic applies
If this logic is not embedded upstream, denial management becomes downstream chaos.
Strong behavioral health EHR and mental health EHR software must align documentation, billing rules, and payer requirements before a claim is generated.
Clean Claims Are an Architectural Outcome
High clean-claim rates are not achieved by working harder.
They are achieved by designing systems where:
- Documentation aligns with billing requirements
- Service types control form type automatically
- Revenue codes are required when necessary
- Payer rule tables are embedded
- Eligibility carve-outs are detected before submission
This approach reflects the concept of claims hygiene in behavioral health billing, where payer rules and documentation logic are enforced upstream.
When infrastructure is correct, denials decline structurally.
When infrastructure is weak, billing teams become firefighters.
Utilization Is Revenue, Not Just Scheduling
A second infrastructure blind spot is provider utilization.
Behavioral health revenue is directly tied to:
- Delivered units
- Authorization alignment
- Cancellation management
- Provider productivity
If your system cannot measure utilization accurately, it cannot optimize revenue.
In percentage-based revenue models, this alignment becomes even more critical.
Structured clinical documentation, including AI-assisted progress notes for behavioral health, can also support payer-aligned billing accuracy and improve clean claims performance.
The Shift That’s Coming
The era of disconnected tools is fading.
Documentation, billing logic, and utilization reporting must converge into a single revenue-intelligent engine.
Behavioral health is becoming more complex, not less. Medicaid programs are expanding. Multi-discipline care models are growing. Compliance scrutiny is increasing.
Infrastructure must mature accordingly.
The practices that win over the next decade will not simply document well.
They will design their revenue systems deliberately.
Organizations building scalable behavioral health infrastructure increasingly rely on integrated systems such as DENmaar’s behavioral health platform.
No hype.
No promises.
Just structural clarity.
Frequently Asked Questions
Why do many behavioral health EHR systems struggle with complex billing?
Many EHR platforms were originally designed for documentation rather than revenue cycle management. When organizations add services like IOP, CMHC programs, or Medicaid-based care, the billing complexity exceeds the system’s original architecture.
What is the difference between CMS-1500 and UB-04 billing in behavioral health?
CMS-1500 forms are typically used for professional services such as therapy and psychiatry. UB-04 forms are used for institutional services such as IOP or facility-based care where revenue codes and type-of-bill fields are required.
What is behavioral health claims hygiene?
Claims hygiene refers to structuring documentation, payer logic, eligibility verification, and billing rules so that claims are correct before submission, reducing denials and improving clean claim rates.
Why is revenue cycle infrastructure important for Medicaid behavioral health billing?
Medicaid behavioral health programs often include carve-outs, unique modifiers, HCPCS codes, and authorization rules. Without integrated infrastructure inside the EHR and billing workflow, practices experience denials, delays, and revenue leakage.
Our Partners






Ready to get started?
Feel free to reach out if you have any questions.
